
In Vivo BLI/FLI Imaging + CFT: A Complementary Approach to Biodistribution Data
Bioluminescence imaging (BLI) and fluorescence imaging (FLI) are the two most widely used forms of 2D in vivo optical imaging in preclinical research. Both let researchers track a labeled cell population, pathogen, or probe in a living animal over time, without a terminal procedure at each timepoint. Both are also 2D projections, which means neither resolves anatomical depth or the fine sub-organ detail that a study's endpoint often depends on. Cryo-Fluorescence Tomography (CFT) is built to complete that picture. Performed at a terminal timepoint, CFT co-registers 3D fluorescence data with high-resolution anatomical imaging, adding the localization and sensitivity that BLI and FLI cannot provide on their own.
Where BLI and FLI Lead
Bioluminescence: near-zero background, ideal for longitudinal tracking. CFT needs a fluorescent label alongside it to visualize the signal.
Fluorescence: broader probe compatibility, more off-the-shelf reagents.
Both: non-terminal, whole-body imaging over time.
The Limit They Share
Both are 2D projections. Neither resolves where a signal sits in three dimensions.
A signal near the surface and one several millimeters deep can look identical in a planar image.
When a conclusion depends on which organ, or which structure within an organ, a signal reached, a 2D projection alone isn't enough.
What CFT Adds
A 3D fluorescence volume co-registered to high-resolution anatomical images, slice by slice.
Performed ex vivo at a terminal timepoint, not a substitute for longitudinal tracking.
Answers where, anatomically, a signal has ended up, at a resolution a planar image cannot reach.
A Combined Workflow, Not a Replacement
Most biodistribution and pharmacokinetic studies benefit from both. BLI or FLI carries the non-terminal, whole-body screening across the length of a study, in the same animal, at a lower cost per timepoint than most alternatives. CFT is added at the terminal timepoint to add the 3D anatomical resolution and sensitivity that a planar image cannot capture. Neither modality replaces the other. Used together, they close the two gaps, longitudinal tracking and anatomical resolution, that neither one closes alone, and researchers reach findings that neither modality could reach by itself.
What CFT and In Vivo Imaging Have Found Together
Five studies where combining a 2D in vivo optical method with CFT's 3D anatomical resolution produced an answer neither modality reached alone.
Refining Localization of a Fibrin-Targeting Peptide
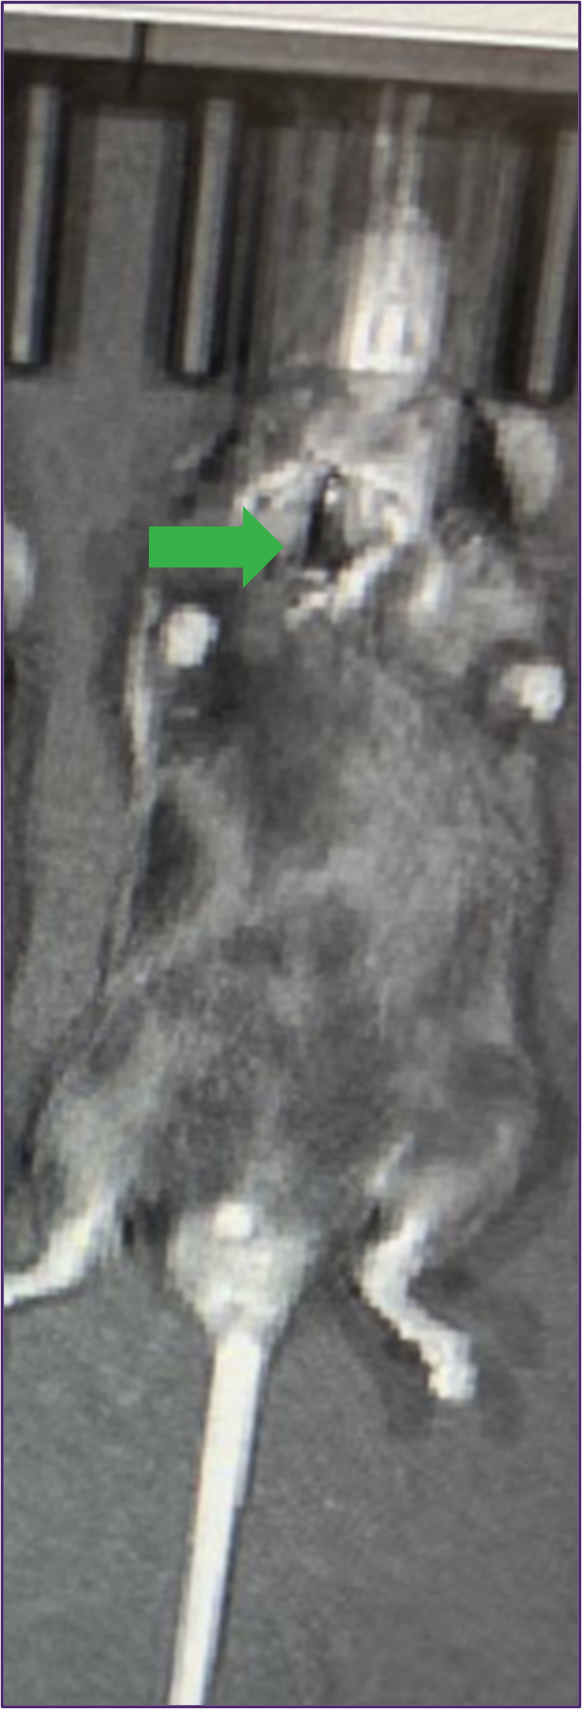
FeCl3 Thrombosis ModelIn a murine FeCl3-induced thrombosis model, a Cy5.5-labeled fibrin-targeting peptide (EP-2105) was injected via tail vein and imaged 10 minutes later. In vivo fluorescence imaging flagged strong signal near the injury site, a promising early read on target engagement. CFT's anatomical co-registration completed the picture: the thrombus was confirmed in the high-resolution anatomical image, and the fluorescent signal was localized to the submandibular gland rather than the thrombus itself, a distinction the 2D image alone could not make.
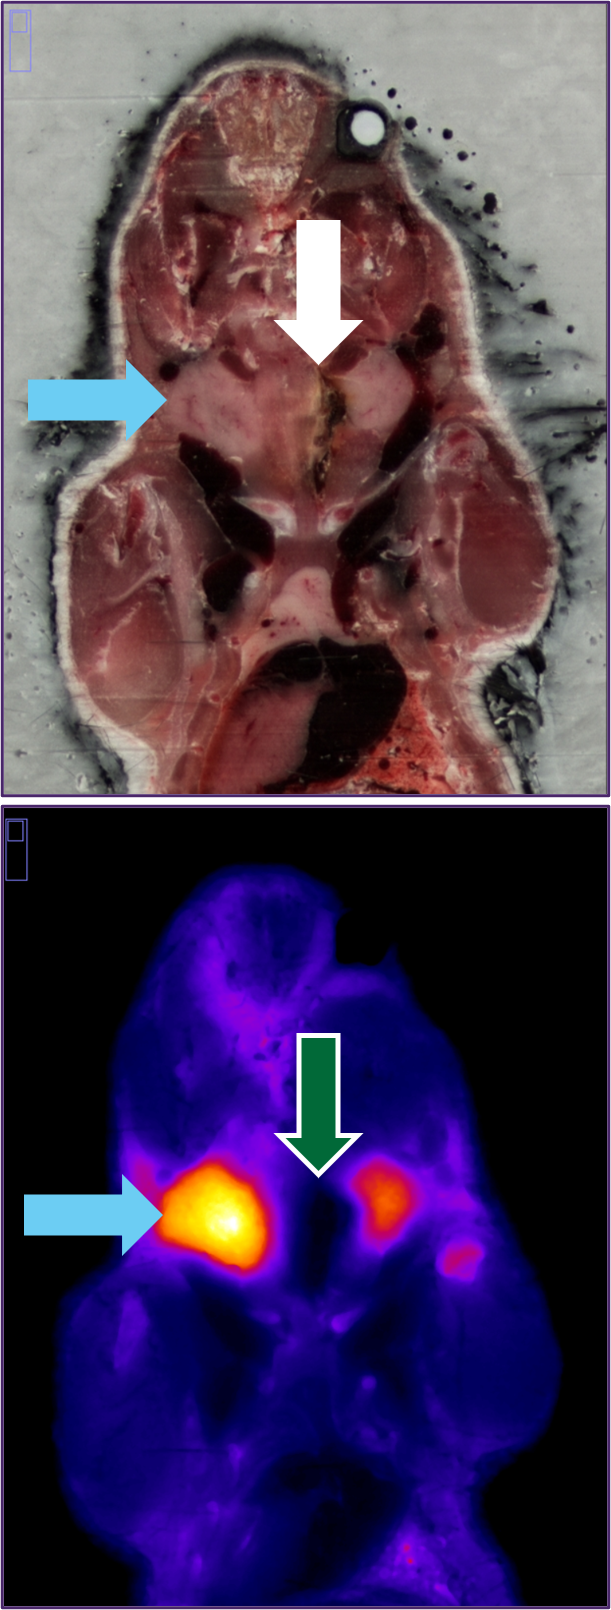
Data provided by Junfeng Wang, PhD, Gordon Center for Medical Imaging, Massachusetts General Hospital, Harvard Medical School.
Detecting Signal a Planar Scan Could Not Resolve
Crush Injury ModelIn a separate vascular crush injury thrombosis model, the same Cy5.5-labeled fibrin-targeting peptide (EP-2105) was administered via tail vein injection and animals imaged 10 minutes later. In vivo fluorescence imaging's limited sensitivity meant no localization to the thrombus was observed. CFT's higher resolution and sensitivity picked up what the 2D scan missed, identifying the peptide signal in the thrombus as expected, adding the confirmation the in vivo image alone could not provide.
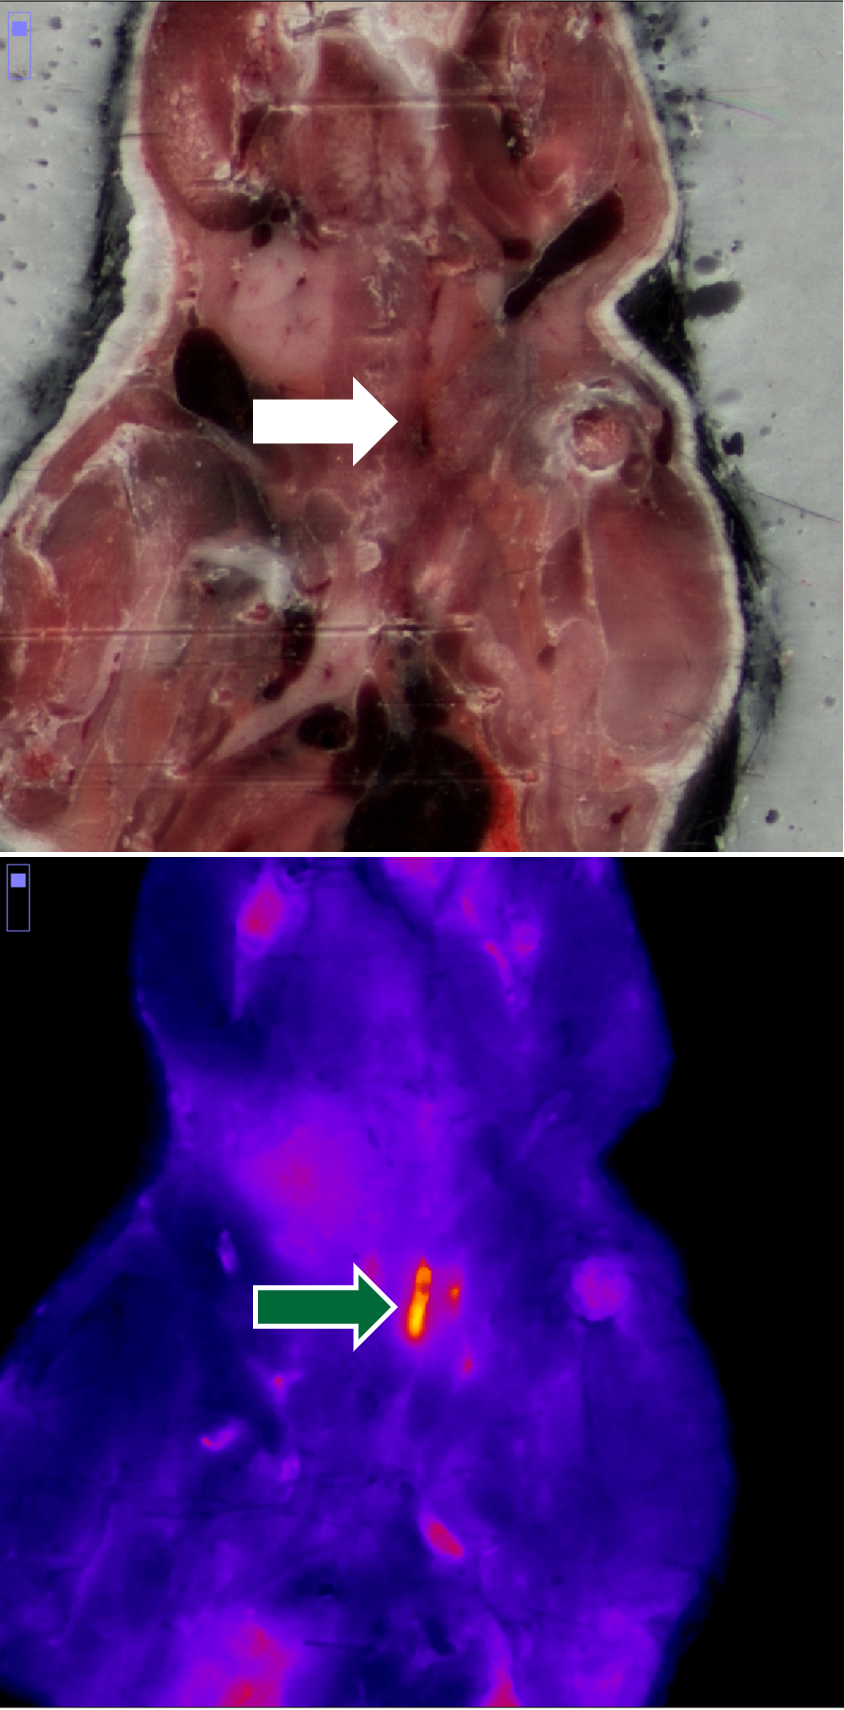
Data provided by Junfeng Wang, PhD, Gordon Center for Medical Imaging, Massachusetts General Hospital, Harvard Medical School.
Confirming Drug-Tumor Co-Localization in 3D
Ovarian Cancer ModelIn an orthotopic ovarian cancer model using tdTomato-expressing tumor cells, animals received an intravenous HER2-targeted antibody labeled with AF647. In vivo fluorescence imaging located the tumor burden and confirmed the antibody had reached it, across the whole animal, over time. CFT added the resolution to see how completely: its 3D reconstruction showed the AF647 signal co-localizing with the tdTomato tumor volume in high resolution, confirming target engagement throughout the tumor rather than its surface alone, a multiplexed, 3D view neither modality could produce by itself.

Tracing Whole-Body ASO Distribution
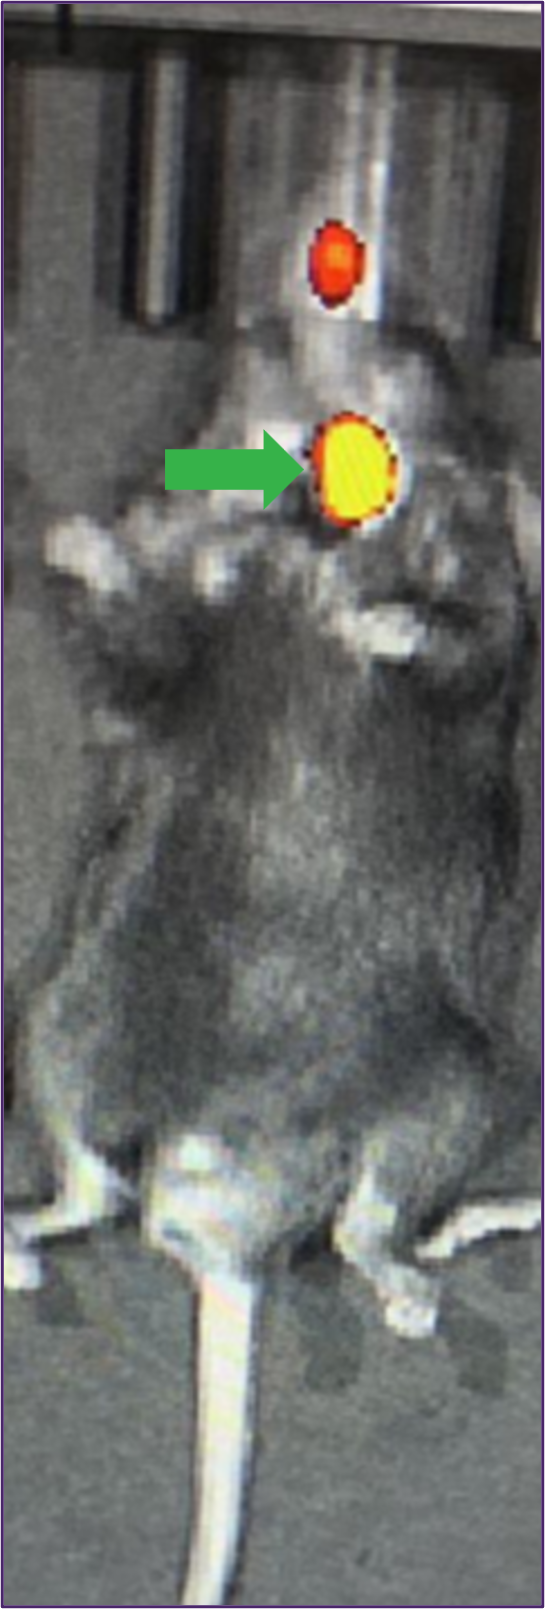
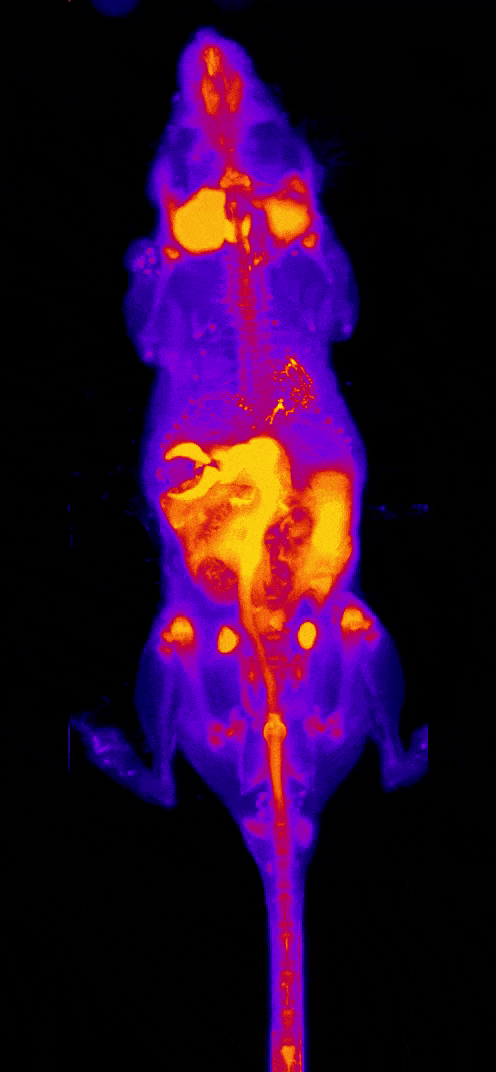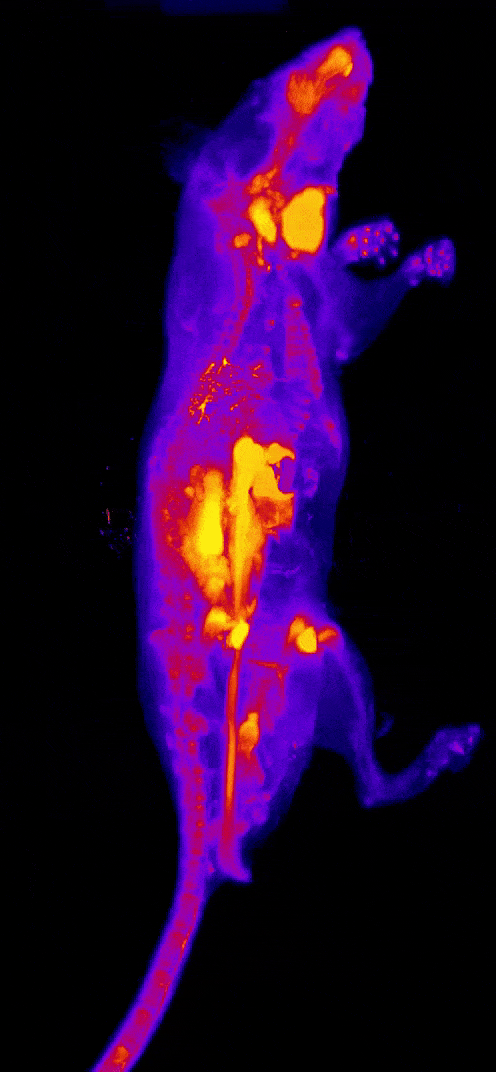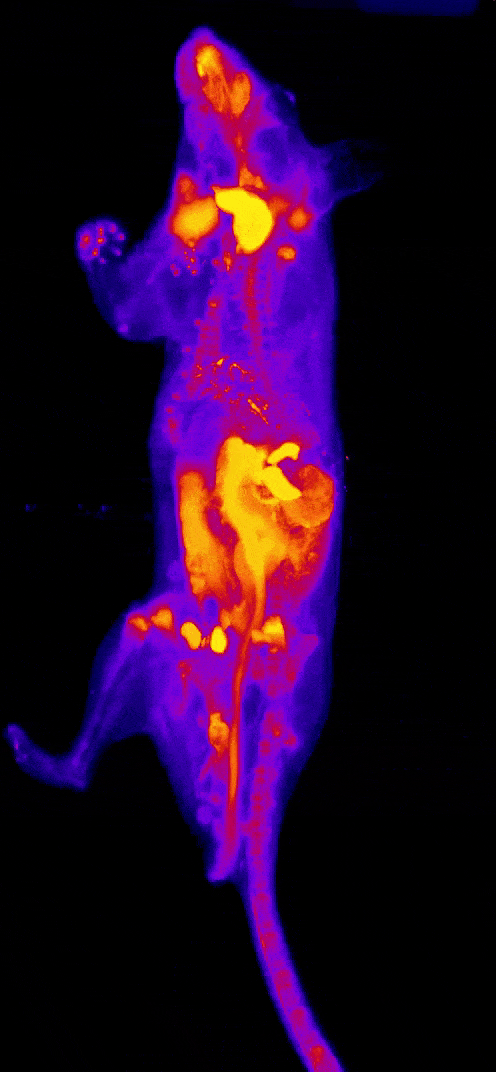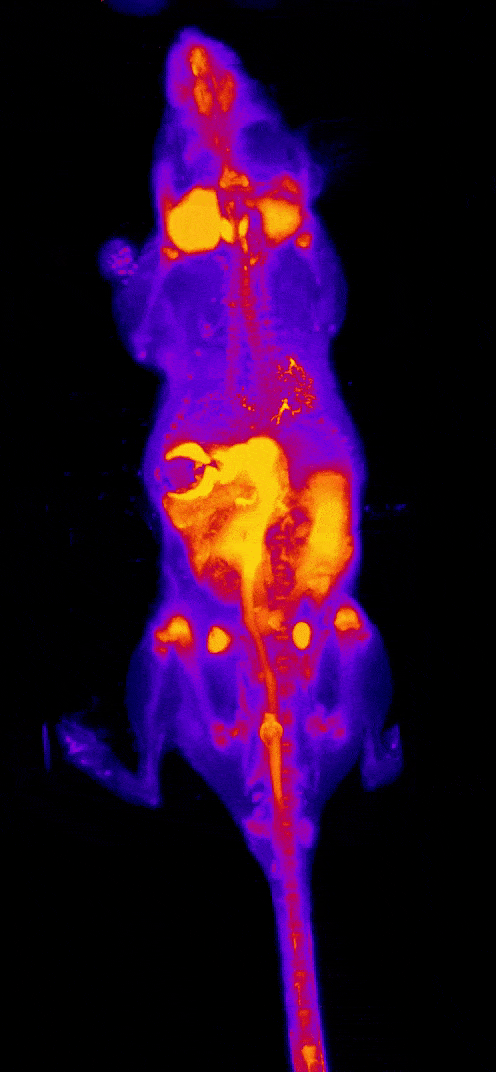
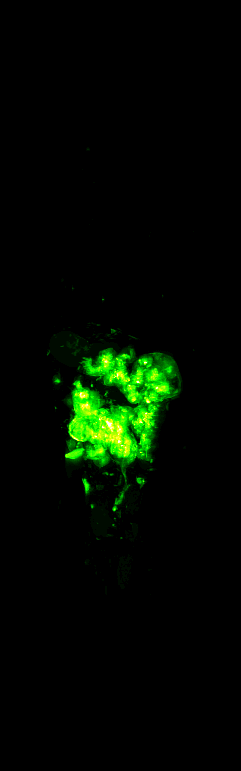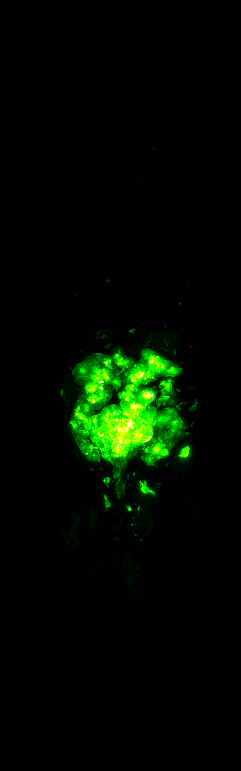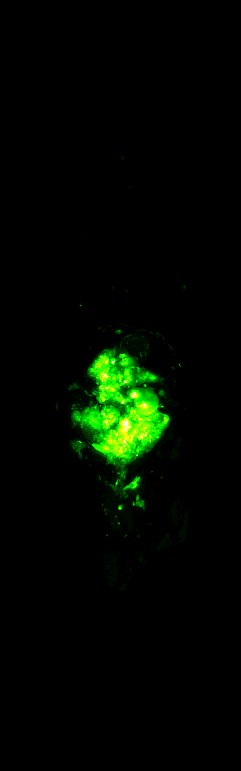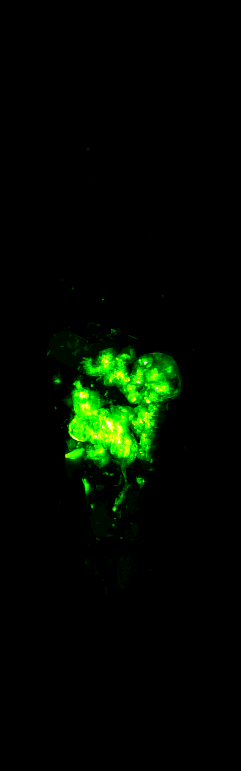
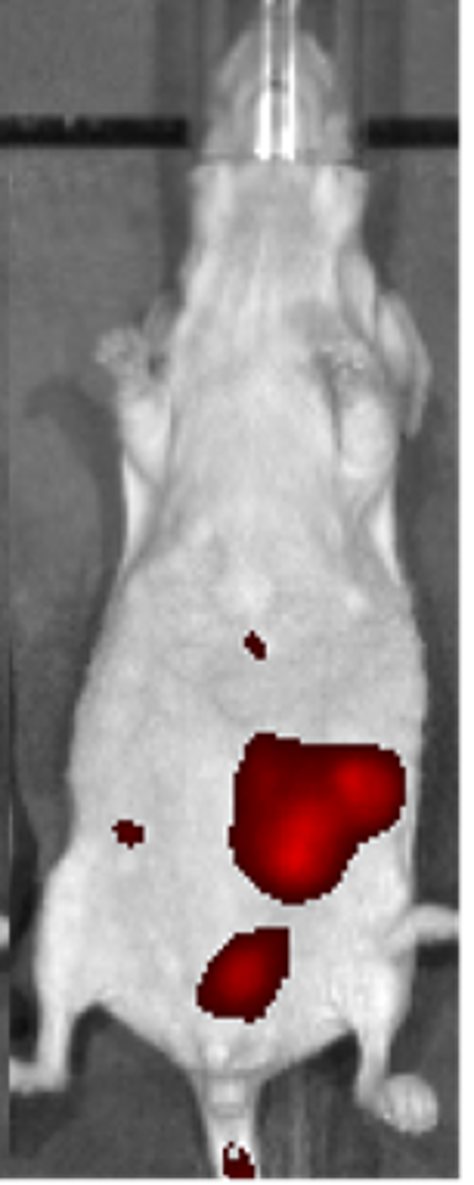
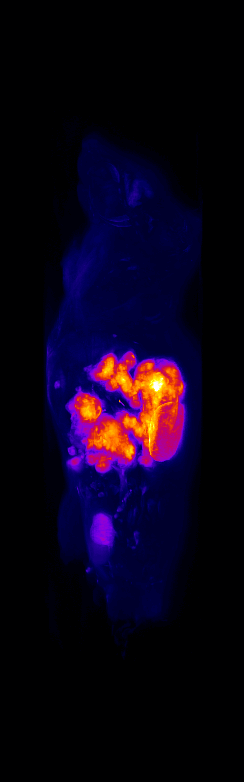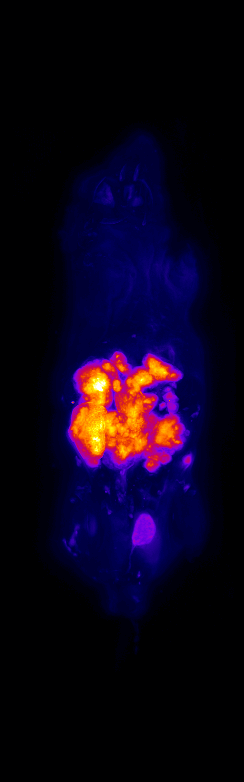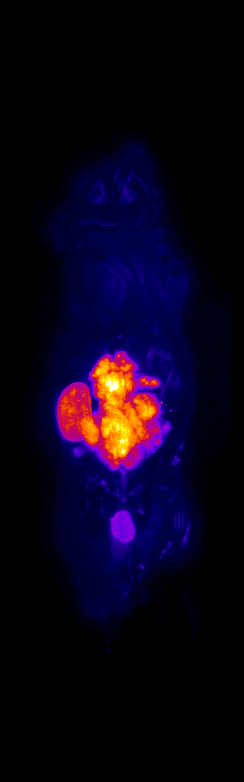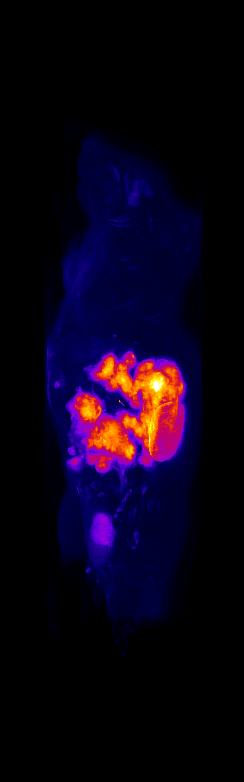
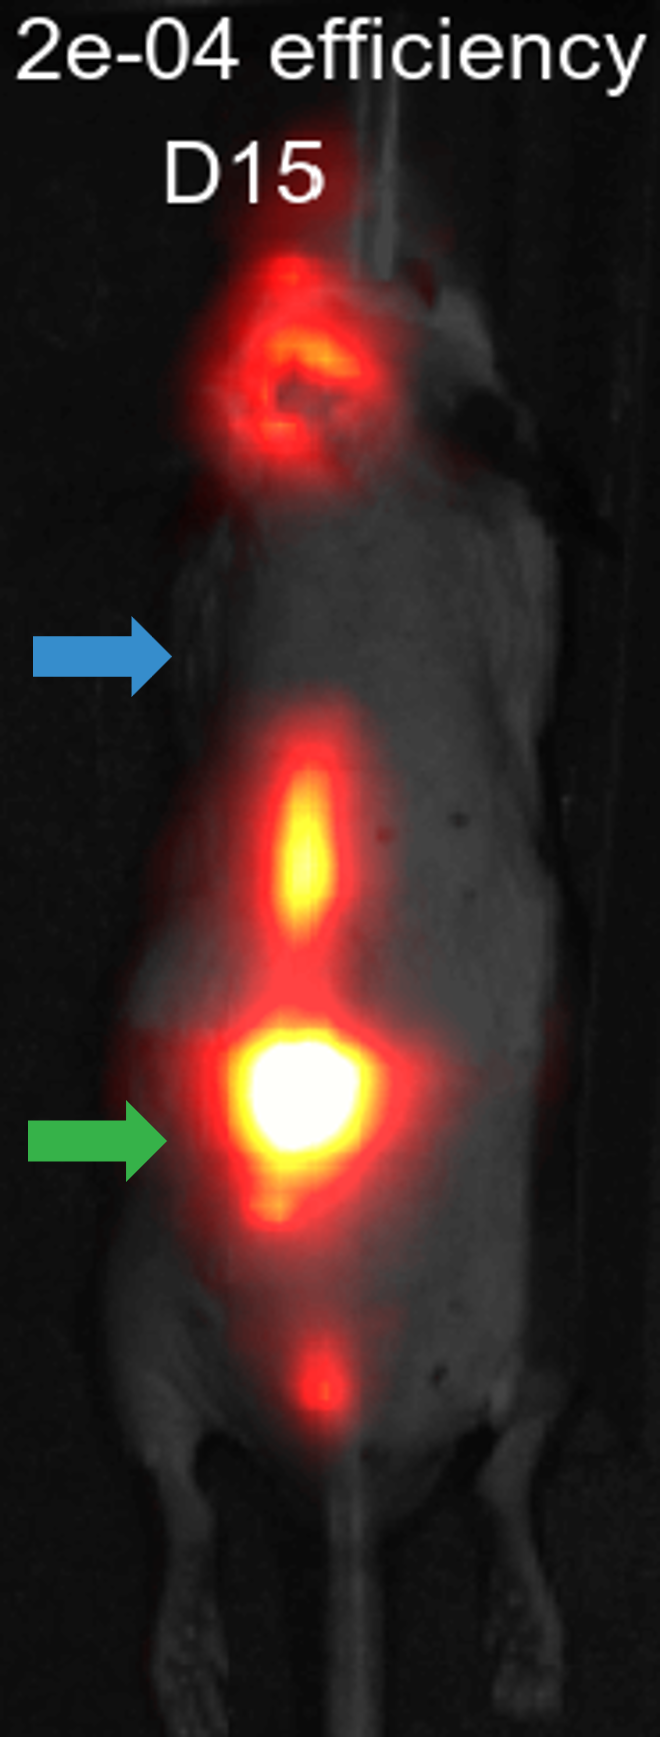
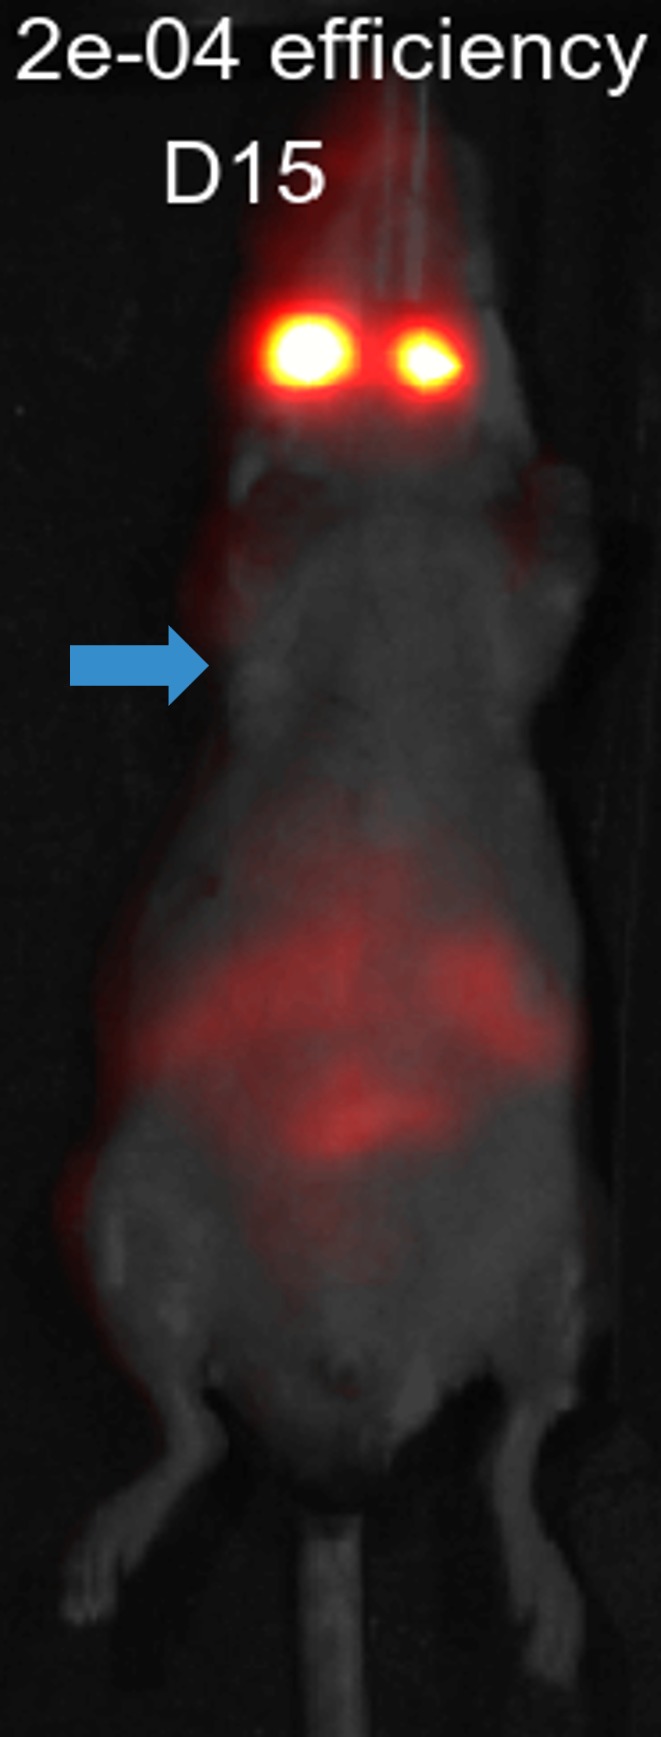
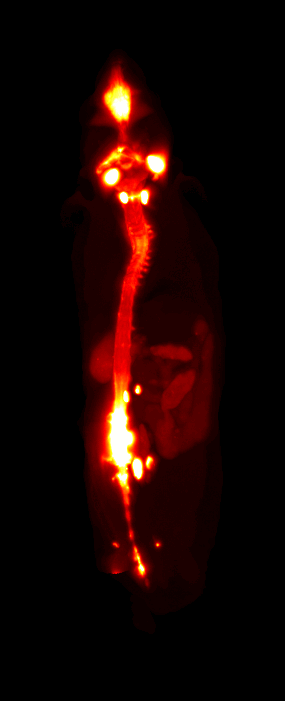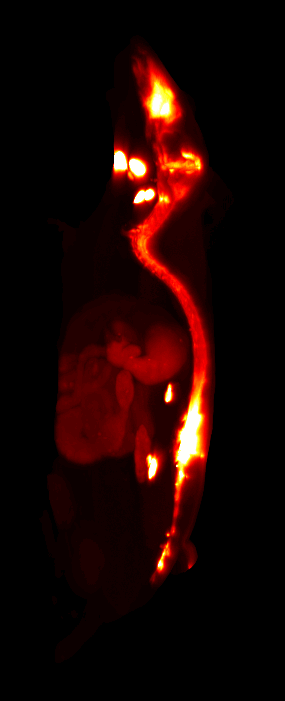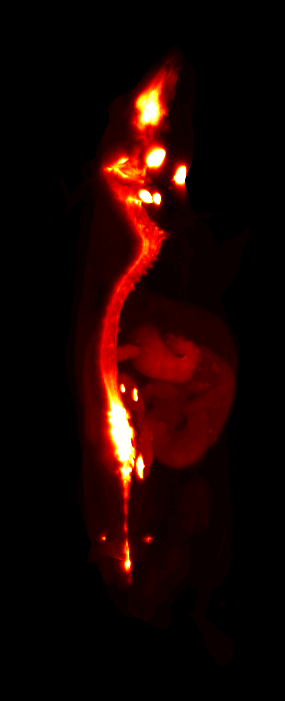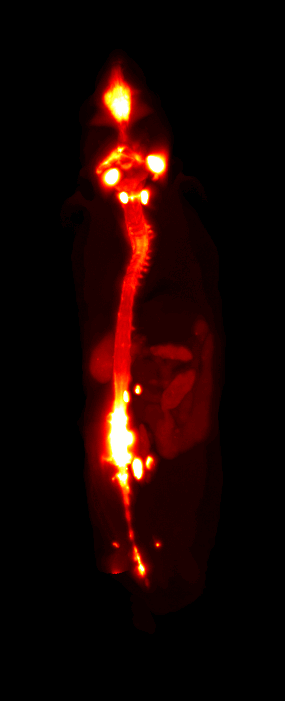
Intrathecal InjectionFollowing intrathecal injection of a Cy5-labeled antisense oligonucleotide, animals were imaged 15 days later in both prone and supine positions. Surface fluorescence imaging showed signal at the injection site and along the spine, tracked non-invasively in the living animal, but lost signal with depth and could not resolve structures below the surface. CFT is unaffected by that depth limit: its 3D reconstruction visualized the full spinal column into the cisterna magna and detected biodistribution and clearance through the GI tract, lymphatics, and nasal turbinates, at sub-50-micron resolution, structures the in vivo images alone could not reach.
Characterizing Metastatic Disease Alongside BLI
Breast Cancer MetastasisMDA-MB-231 human breast adenocarcinoma cells, engineered to express both firefly luciferase and DsRed, were implanted in mice. In vivo bioluminescence imaging tracked the flank tumor's growth over time in the living animal, a longitudinal view CFT cannot provide. The DsRed fluorescent label was added alongside the luciferase reporter specifically so CFT could visualize the tumor at the terminal timepoint. CFT cannot image a BLI signal on its own; it requires a fluorescent counterpart. At that timepoint, CFT's 3D DsRed reconstruction added what BLI's whole-body signal alone could not: the primary tumor's extent and internal heterogeneity, plus metastatic lesions in the lungs. Together, the two modalities gave a complete picture, growth over time and anatomical extent at the endpoint, that neither could have produced alone.
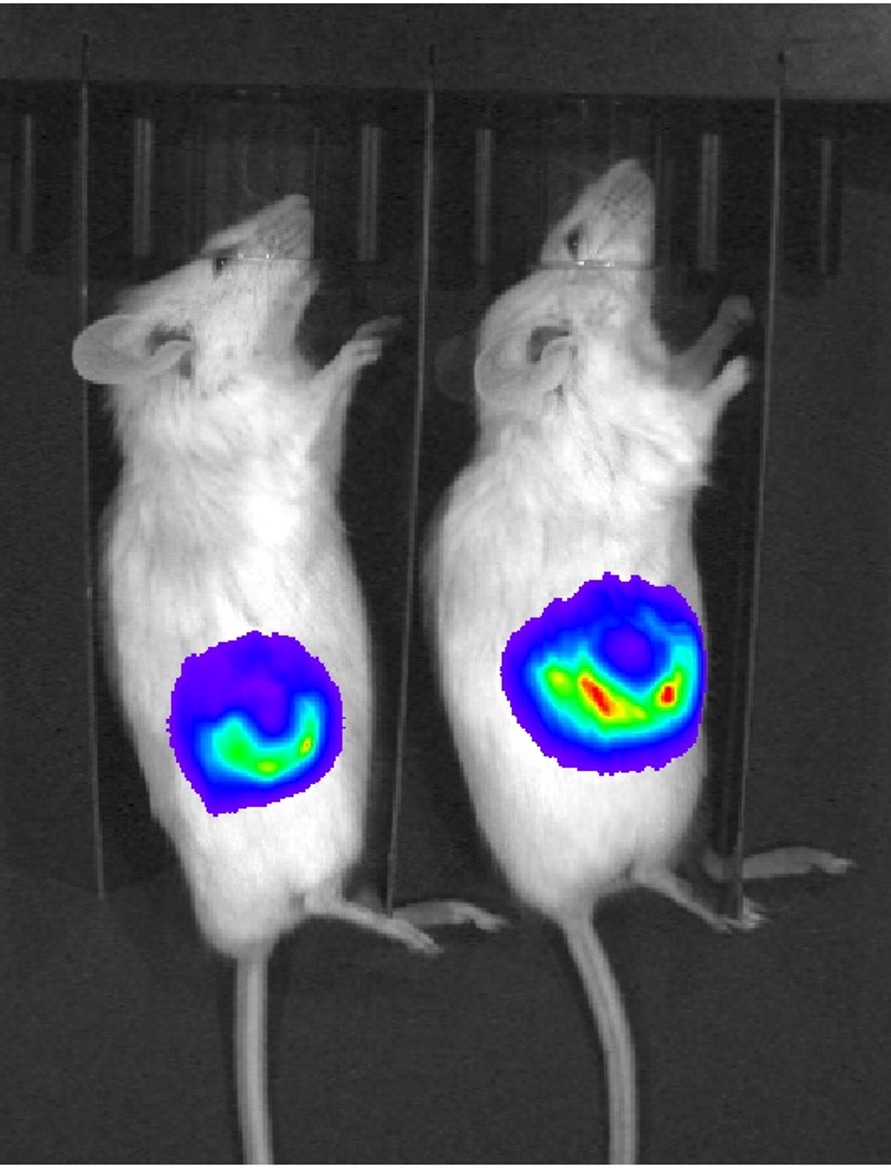

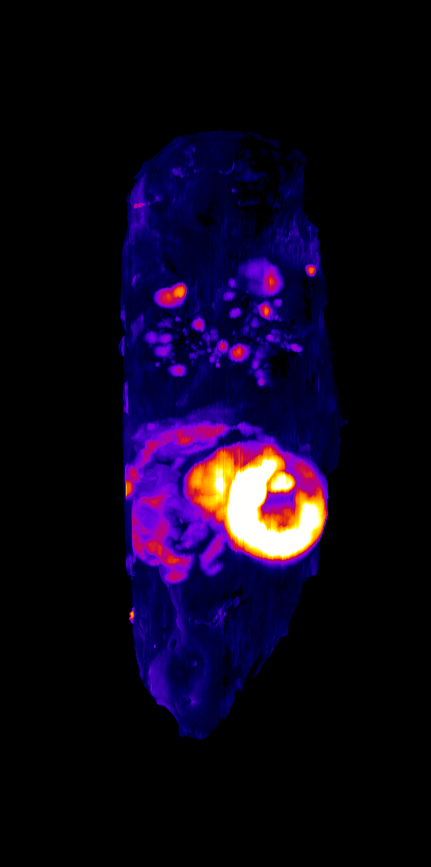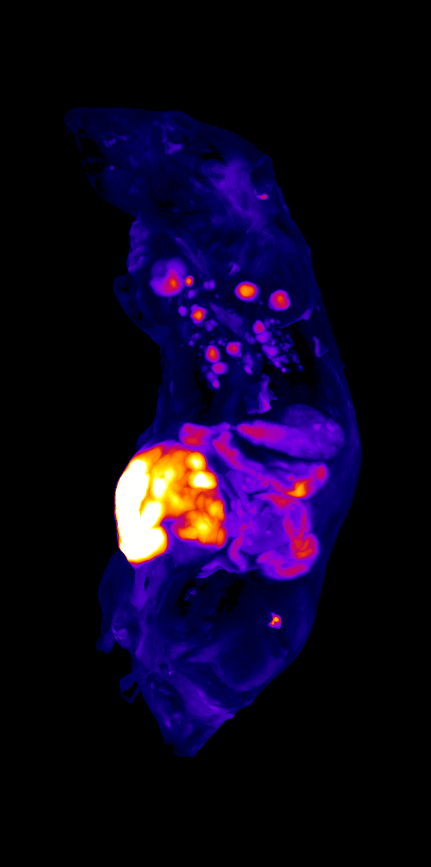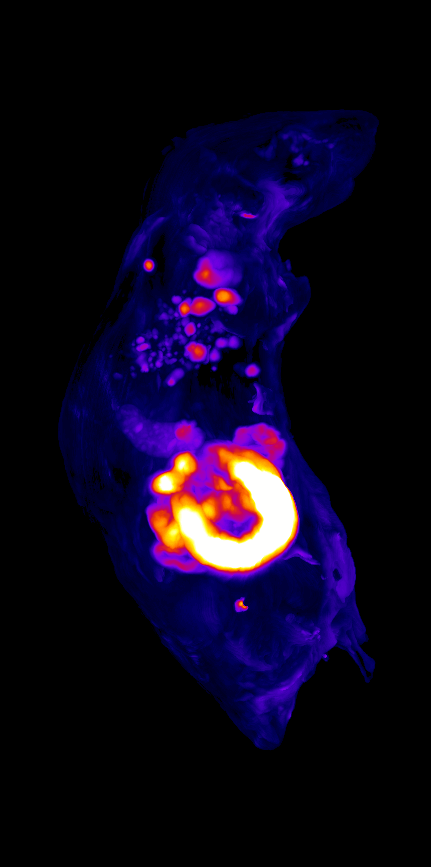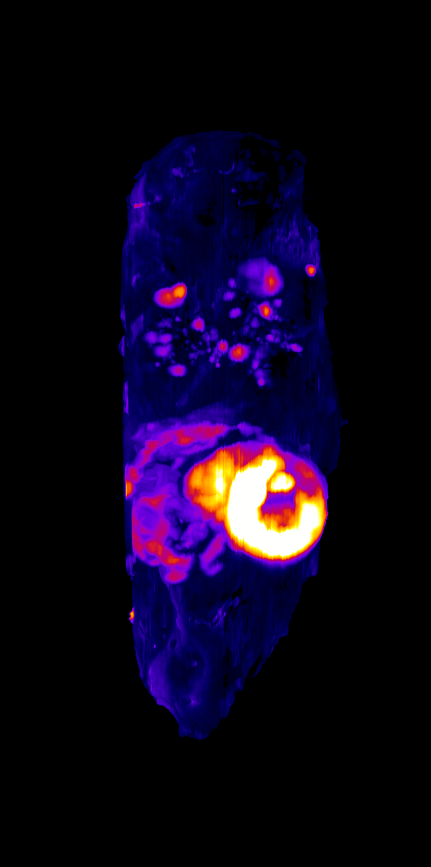
DsRed mice provided by John Ronald, Robarts Research Institute.
The fibrin-targeting peptide findings above are drawn from a full case study comparing CFT with 2D in vivo fluorescence imaging. Read the case study →
What is the difference between BLI and FLI in vivo imaging?
BLI detects light generated by a luciferase reporter and its substrate, giving very low background signal. FLI detects light emitted by a fluorophore that has been excited by an external light source, offering broader probe compatibility. Both are 2D optical imaging methods used to track signal in a living animal over time.
Does CFT replace in vivo BLI or FLI imaging?
No. CFT is a terminal, ex vivo step that adds 3D anatomical localization and higher sensitivity. It is designed to work alongside BLI and FLI, not instead of them.
When should CFT be added to a biodistribution study?
CFT is typically added at the study's terminal timepoint, once in vivo BLI or FLI has completed its longitudinal screening, to confirm or refine the anatomical location of a probe, cell population, or therapeutic candidate.
Can CFT be used with existing in vivo imaging data?
Yes. CFT is commonly used as a confirmatory or follow-up step to data already collected on in vivo optical imaging platforms.
Can CFT image a bioluminescence (BLI) signal directly?
No. BLI relies on a luciferase reaction rather than fluorescence, and CFT is a fluorescence-based technique. To visualize a BLI-tracked model with CFT at the terminal timepoint, the animal must also carry a fluorescent reporter or label alongside the luciferase.
CFT Imaging Alongside Your In Vivo Workflow
EMIT Imaging provides CFT as fee-for-service imaging, run at our labs alongside your existing BLI and FLI in vivo workflows, or as instrumentation on the Xerra™ platform for in-house use.